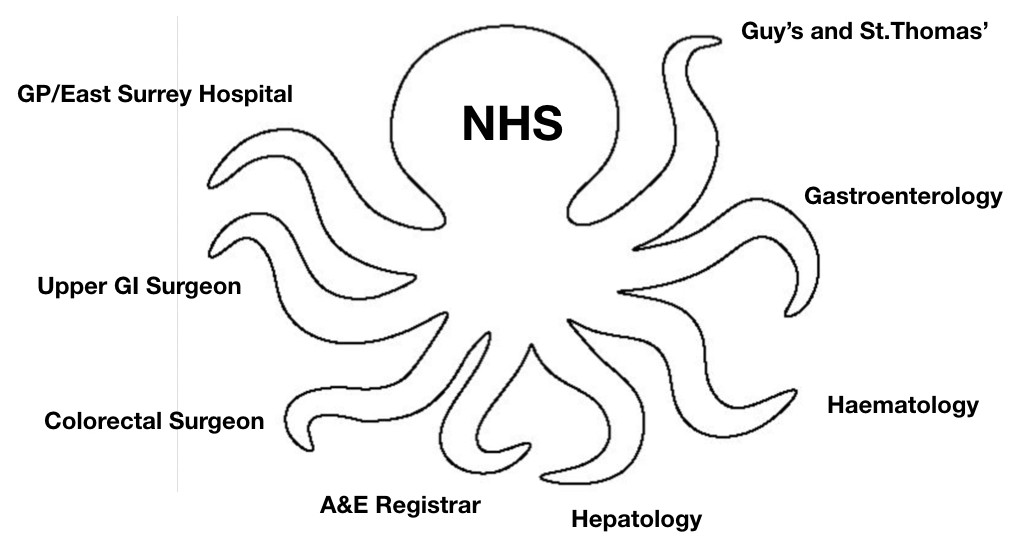
A blog post or the start of a potential chapter for another book? Is it IBD related? Probably. IBD patients are more at risk of developing stones (urolithiasis) and that is what triggered this post.
Disclaimer : By the very nature of the subject it may contain details that some readers would consider TMI!
3rd May – It’s a bright, sunny day. The first Sunday in the month. An early start to head for Redhill to watch the annual London to Brighton Historic Commercial Vehicle run. A chance to see lorries and buses I remember from my childhood and some that my father or grandfather would have recognised.

We spent a couple of hours standing at the top of the long hill out of the town, watching some of the older vehicles struggle to make the climb. When we’d seen enough, it was back home to do a couple of hours gardening before lunch.
By now I was dying for a pee so trotted off to the toilet …and that’s when it happened. Without warning I was passing blood. Not Rosé but Beaujolais Nouveau. I stared in disbelief. The last time I had seen this amount of blood coming out of an orifice was when my oesophageal varices burst, in the same room, back in 2012. On that occasion it was call 999 and get whisked away to A&E in the back of an ambulance.
What should I do this time? I tried ringing 111 but couldn’t get a reply. In desperation I rang 999 who advised me to head for the Urgent Treatment Centre at Crawley Hospital. I was hoping to avoid a visit to A&E but the triage nurse at the UTC quickly put paid to that one and said “Go to East Surrey Hospital A&E”.
On arrival in A&E the screen showed an average 4 hour wait until being treated. This gradually reduced and finally it was my turn to see the doctor. I’m very grateful to my sister who came with me so that I had someone to talk to whilst we waited. By now my urine was returning to normal and I was wondering if I had over reacted. The doctor didn’t seem too concerned but said that my GP should put me on the “two week” wait list to see a urologist. The mention of “a two week list” is always enough to stop me in my tracks… and with that thought I left the hospital just before 11pm.

After the “Beaujolais Nouveau” experience the battle between my brain and bladder started. My brain was saying “I don’t want to see any more blood so don’t pee”; my bladder was saying “I’m full, you need to pee”. Is there a bladder – brain axis? Obviously the bladder won but every time I went to the bathroom it was with a lot of trepidation. Slowly this subsided as time wore on and no more blood appeared but would it return?
Following my visit to A&E I waited a couple of days before calling into my GP surgery to ensure an urgent appointment had been requested and soon afterwards a date for a CT Urinary Tract with contrast came through. 28th May, not quite 2 weeks but pretty close. The scan itself went without a hitch.
A few days later one of the urology nurses rang me. The scan showed stones in my bladder. Next step? A flexible cystoscopy. Could I make an appointment on 3rd June? Yes I could but wanted to know what was involved. She explained that a flexible scope would be passed into my bladder and the images would appear on a screen above the bed. Some patients found it “quite interesting!”
3rd June – the day of the cystoscopy arrived. My wife came with me. We sat in the urologist’s office and ran through our list of questions. It was then time to disappear behind a curtain, lay down on the bed and drop my trousers. The urologist applied some local anaesthetic to the relevant appendage and then proceeded to insert the scope. It’s making me squirm just writing about it. Despite the anaesthetic it was quite painful. The pictures appeared on a small screen above me and, to be honest, it was quite interesting. The urologist gave a running commentary and showed me three bladder stones of varying sizes. They would need to be removed.
That’s when we first heard the term cystolitholapaxy. She explained that the procedure would involve breaking up the stones with a laser and then flushing the debris out. It would be carried out under a general anaesthetic and was usually a day case.
Her final words were “I realise that it’s not always easy but you need to drink at least 2 litres of water a day to keep your system flushing through”. What goes in has to come out and it was painful. The brain – bladder battle restarted and lasted a few days.
Back in 2019, just before COVID I started a role of patient representative for a study investigating ways of improving shared decision making with “elderly, high risk patients about to undergo surgery”. I am now firmly in the “elderly’ category, whichever way you measure it, and considered “high risk” due to my myriad co-morbidities. As I would be undergoing a general anaesthetic a meeting was arranged with an anaesthetist.
16th June – he answer to “would the blood return?” was “Yes it would”, just as I was about to have an endoscopy with ultrasound at St.Thomas’ Hospital in Westminster. I was probably dehydrated as you cannot drink for six hours before scoping. (The reason for needing an endoscopy wih US head will be the subject of another post, one day)
3rd August – the appointment with the anaesthetist. She ran through the whole range of “elderly” questions starting with the usual “can you dress yourself?”; “can you climb a flight of stairs?”; “do you get out of breath walking?”. We then turned to co-morbidities. I mentioned that I have portal vein thrombosis and low platelets, In preparation for the meeting I had emailed my consultant at St.Thomas’ regarding the procedure as some patients are given blood thinners but this might not be appropriate in my case. Could she please contact him to discuss any special precautions that needed to be taken.
A few days later Surgical Appointments rang with a proposed date for the procedure of late October. Checking my diary it was very close to one of my 8 weekly vedolizumab infusions at Guy’s. As I didn’t know how I would feel after the general anaesthetic I wanted to try and get a date shortly after an infusion. Would it be possible to time it so it was just after my next infusion on 10th September? We agreed a date of Saturday 19th September.
5th September – the next step was a blood test. I took the opportunity to ask if contact had been made with my thrombosis consultant at St.Thomas’. The nurse checked my record and confirmed that it had. That put my mind at rest and showed that I had been listened to.
12th September – one final hurdle, a urine test. All OK so just a week to wait. I had done what I’m sure we’d all do and Googled “cystolitholapaxy” but made sure I didn’t look at any images or videos.
I then had another incident, but not like the last two. This time mid pee everything just stopped. Nothing more would pass. I felt this tremendous pressure building up then a searing pain. What was happening? It didn’t take long to find out. A large bladder stone appeared. I was shocked at the size of it. How the hell did that escape? Without going into the details I did manage to retain the stone and, after thoroughly disinfecting it, measured it. See the photo below!

15th September – Surgical Appointments rang. They had a number of urgent cases and were proposing to put my procedure back a few weeks. I protested that I was also urgent, explained the timing issue with my infusion and that the anaesthetist had already been in contact with my thrombosis consultant to discuss the particular risks I presented. If the procedure was postponed then all these would need to be gone through again. It was agreed to keep to the original date…..but they might call me later in the week! She added that whilst the original letter said “day case” she would change that to an overnight stay. I spent the rest of the week expecting a postponement. It never came.
19th September – the pre-op instructions said to report to the Surgical Admissions Unit at 7:00. There was a small queue waiting but we were quickly admitted and asked to take a seat in the Lounge.
A triage nurse went through the standard admission questions and explained that the surgeon would discuss the procedure, go through the risks and get the consent form signed. He then appeared and we went into his office to get the pre-op formalities done. As I left his office the anaesthetist approached and introduced himself. He hadn’t been expecting me until that afternoon. I was fourth on the day’s list and was expected to go into theatre at 12:00. We discussed the administration of the general anaesthetic and my thrombosis issues.
I returned to the waiting lounge and it was still only 8:00am! Luckily I had a book to read as I had experienced a similar wait when I had my stoma reversed, many years ago. The lounge quickly emptied and I was left there all on my own.
At 11:30 the wheels started to turn. Off to the pre-op ward, on with a hospital gown (with the inevitable missing tie), a pair of compression stockings (with those annoying holes which your big toes get stuck through) and get onto the bed. I was then wheeled to the anaesthetic room where I was greeted by the anaesthetist. In my experience anaesthetists are happy souls and put you at your ease. A cannula was quickly inserted. We discussed which cocktail of drugs he would be using to knock me out. I can’t remember the names but it would be a more powerful version of the fentanyl/midazolam mix that I have become so used to when I have an upper GI endoscopy. Instead of the usual “count to ten but you won’t make it past three” he said “this should take a couple of minutes to take affect”. He injected the cocktail and I was very quickly under.
“Where am I?” “You’re in Recovery. When you’ve come round sufficiently we’ll take you to the ward in the Surgical Centre”. I could see that there was a catheter and bag. That was to be expected. What I hadn’t experienced before were the auto inflating compression sleeves wrapped around my legs.
Off to the ward. It was empty! A 4 bay ward and I was all on my own. This had to be the quietest ward I’d ever stayed on. I now had a chance to roll back the blanket and see the catheter properly for the first time. I was in for a shock! I’ve experienced them before but this one was huge. How did it even fit? Thank heavens it had been inserted under general anaesthetic. It appeared to be working as the bag was slowly filling with Rosé.
After an hour or so another patient was brought in. It turned out that he lived in the next village to us. We had plenty in common to talk about whilst passing the time. I asked a nurse why it was so quiet. She explained that usually this ward was only open Monday to Friday but they had four patients that needed to stay overnight from their Saturday procedures so it had been opened even though they had struggled to find sufficient staff to cover.
The nurse told me to drink lots of water which was fine until my catheter became partially blocked. A quick flush through with some saline solution solved the problem. Then, during the night, it became completely blocked so instead of the urine passing down the inside of the tube it forced its way along the outside which was not only uncomfortable but soaked the bed. At first the night staff did not attempt to flush it through but gave me some absorbent pads to soak up the leakage. Not really a solution. Luckily a nurse appeared who did know how to flush a catheter and that again solved the problem
Any chance of getting to sleep was made impossible by the DVT sleeves around my lower legs. They were constantly inflating and deflating in a seemingly random pattern.
Once I had eaten breakfast my mind turned to when I might be able to go home and, more worryingly, how the catheter would be removed. The answer to that last question was deflate the balloon that holds it in place, by sucking the air out with a syringe, then grab hold of the catheter and pull it out very, very quickly. The nurse had clearly removed a lot of these!
I didn’t know exactly when they would discharge me. At the best of times it can be a lengthy process, waiting for the discharge letter to be signed off by a doctor and the correct medication in place. This inevitably takes even longer at weekends and this was no exception. From past experience I knew that as soon as I changed into my outdoor clothes I would want to be leaving and this just leads to growing frustration. I therefore chose to stay in my hospital gown until late morning and only get dressed just before lunch was served. Finally a doctor was found to sign off the discharge letter and I left hospital at 2pm.
Two weeks later – I felt fully recovered. The discharge instructions were fairly vague. “Most people can return to normal activities within a week”. But I found another NHS document that said “We recommend that you avoid strenuous exercise and heavy lifting for 2 – 3 weeks. You should do lighter exercise, such as walking and light housework, as soon as you feel well enough. Do not drive for the first 2 weeks after the operation.” I think this must have been more generic advice and I certainly didn’t keep to it.
IIn the discharge letter it mentioned having a follow-up appointment with the urologist. That has now been arranged for 23rd December. Would I need any further tests before I saw her? A text arrived with the date for another CT scan, 2nd December, three weeks before the appointment. No trip to hospital needed for this as it will be carried out at the newly opened Redhill Community Diagnostic Centre located in the shopping mall.
I don’t know what to expect when discussing “next steps” at the appointment. Did I mention I have an enlarged prostate? Another co-morbidity, another story…… The surgeon had mentioned that they might need to use a laser to “shave” my prostate down to reduce the pressure on my urethra. I can’t say that the thought of another procedure, and that one in particular, fills me with much enthusiasm!
Footnote – Prior to the cystolitholapaxy I had deliberately not looked at any videos of the procedure. I envisioned some sort of flexible device, like the cystoscope, that made its way into the bladder and could be fitted with various tools. How wrong I was! No wonder it hurt afterwards. The device is rigid and a much greater diameter than the catheters I had previously experienced. It reminds me of the gun that I had been using at home to inject expanded foam.